Fighter Cut › Articles › Fight camp
Fight camp
Injury severity and tissue grade are different things
A grade tells you what the scan showed. It does not tell you when you fight again — and the evidence on how far it shifts that date is thinner, and wider, than the number sounds.
The physio said Grade II. The fighter heard a date. Those are not the same object, and the distance between them is the subject of this article.
A tissue grade describes what the imaging shows about the tissue. Severity, in the surveillance literature, is days unavailable. They are separate axes, measured by different people with different tools, and the correlation between them is weaker than almost anyone in a gym assumes. The strongest single study on the question — 39 hamstring strains at one professional English football club, MRIs re-read by two musculoskeletal radiologists, all male professionals — found that a multiple regression model containing the grade, the length of intramuscular oedema and the percentage cross-sectional area involved explained 16% of the variance in return to play. The grade on its own was weaker than that: r = 0.32, with a 95% confidence interval running from 0.01 to 0.58. The floor of that interval is essentially zero.
That is not an argument that the grade is meaningless. It carries real signal, and later in this article the studies that demonstrate it are laid out in full. It is an argument that the grade is a distribution shifter, not a calendar. And that the question the fighter is actually asking — can I train tomorrow, will I make the card in six weeks — is answered on a different axis entirely, by a person who has examined the limb, and where a bout is involved, by a commission physician. What the frameworks for training around an injury actually offer, and what they were validated on, is a separate question again — and the answer is thinner than the rules of thumb suggest.
The useful thing about combat sports here is that the regulatory apparatus already works this way. It does not ask for a tissue grade. It never has.
Agreement between two accepted grading systems reading the **same 39 MRIs** — near chance. CI 0 to 0.42
Tears et al., Phys Ther Sport 2022
Share of return-to-play variance explained by a model containing grade, oedema length and cross-sectional area, in 39 hamstring strains at one professional English football club, all male
Tears et al., 2022
Mean time to return to full training for rehabilitation-managed rectus femoris injuries — 38 injuries, 27 elite track and field athletes, MRI within 7 days. The SD is 73% of the mean
McAleer et al., Scand J Med Sci Sports 2022
Occurrences of the word "suspension" in the ABC Unified Rules of MMA as amended through 6 August 2025, verified by full-text extraction on 7 September 2026
ABC Unified Rules of MMA
- A grade and a severity are measurements of different things. The IOC's 2020 consensus on recording injury data tells investigators to record severity as the number of days an athlete is unavailable for training and competition, counted from the day after onset through the day before full availability. That is a number known only afterwards.
- The spread inside a single grade is wider than the gap between grades. Rectus femoris injuries in 27 elite track and field athletes returned to full training at a mean of 20.4 days with a standard deviation of 14.8 — a dispersion that is 73% of the mean, inside one dataset with one prescribed rehabilitation protocol.
- In one cohort there was no relationship at all. Across 24 hamstring and 10 quadriceps tears in 21 of 121 collegiate American football athletes (20 ± 1.2 years, 100% male, one institution, one season), the authors reported "no significant relationship between BAMIC and TRTP", with a median return of 26 days and an interquartile range of 17.8 to 33.0 days.
- The label itself is less stable than it sounds. Four fellowship-trained musculoskeletal radiologists with 13 to 27 years of experience, reading 111 acute muscle injury MRIs, agreed at kappa 0.506 for BAMIC and 0.566 for the Munich classification — moderate, in the paper's own words. Two different grading systems applied to the same 39 MRIs in a separate study agreed at kappa 0.21.
- Grade still matters — it just does not name a date. Grade 1 rectus femoris injuries returned significantly faster than grade 2 (p = 0.04) and grade 3 (p = 0.01); intratendinous involvement and surgical management took significantly longer (p < 0.001). Intratendon classes in a British Athletics hamstring cohort took 34 ± 7 days (2c) and 48 ± 17 days (3c) against a whole-cohort mean of 18.6 days.
- The folk timetable has no source. "Grade I is two weeks, Grade II is four to six weeks, Grade III is three months" does not trace to a primary study. It is refuted by the dispersion in every cohort above, and by the null result in collegiate American football.
- The five-label IOC severity scheme is a misattribution. The 2020 IOC consensus recommends continuous days and, where categorisation is unavoidable, four bands: 0 days, 1–7, 8–28, and more than 28. Slight / minimal / mild / moderate / severe belongs to the older football-consensus lineage, not to the current IOC statement.
- No commission anywhere keys a suspension to a tissue grade. The structure, wherever it was checked, is an event-outcome minimum plus a physician's judgement of fitness — and the physician's decision is final.
- None of the grade-versus-time evidence comes from a combat sport. There is no muscle-injury grading-to-return-to-play cohort in MMA, boxing, Muay Thai, BJJ, wrestling or judo. The entire base is football, track and field, and American football, in adult and mostly male athletes with full-time medical support.
What a grade is actually measuring
Start with what the systems say about themselves, because the definitions settle most of the confusion.
The British Athletics Muscle Injury Classification, published in the British Journal of Sports Medicine in 2014, grades injuries 0 to 4 based on MRI features, with grades 1 to 4 carrying an additional suffix — 'a', 'b' or 'c' — if the injury is myofascial, musculo-tendinous or intratendinous. Two things follow immediately. The first is that it is an MRI-based system: without imaging, the object the system defines does not exist. The second is that the letter is an anatomical site, not a size. It says where in the muscle–tendon unit the injury sits, not how much of the muscle is involved.
The Munich consensus statement, published a year earlier by a panel of 30 native-English-speaking scientists and team doctors of national and first-division professional teams, splits injuries differently. On one side sit functional muscle disorders — type 1 overexertion-related, type 2 neuromuscular — in which there is no macroscopic fibre tear at all. On the other sit structural muscle injuries: type 3 partial tears, type 4 (sub)total tears and tendinous avulsions. Within type 3, the dividing line is explicit and physical. Type 3A, a minor partial tear, is a "[t]ear with a maximum diameter of less than muscle fascicle/bundle". Type 3B is a "[t]ear with a diameter of greater than a fascicle/bundle".
Read that threshold again, because it is the answer to one of the most common misreadings in the gym. The 3A/3B line is a fascicle-width threshold on an image. It is not a percentage of the muscle, and it is not a functional threshold, and it is certainly not a time threshold. Nothing in either system defines a grade by how much of the muscle cross-section is torn.
Both systems exist because their authors thought the older three-grade scheme was inadequate. The BAMIC paper is blunt about it: "The commonly used muscle injury grading systems based on three grades of injury, representing minor, moderate and complete injuries to the muscle, are lacking in diagnostic accuracy and provide limited prognostic information to the clinician." The Munich statement makes the complementary point: "The limitations of the previous grading systems are a lack of subclassifications within the grades or types with the consequence that injuries with a different aetiology, treatment pathway and different prognostic relevance are categorised in one group."
That is the field's own verdict on the scale most fighters are still quoted. And it is worth noting that BAMIC was published ahead of its own validation — the 2014 paper describes validation studies as "underway".
Where "Grade I, II, III" came from
The three-grade sprain scale that everybody uses conversationally is older than either of the imaging systems, and older than imaging as a routine clinical tool. It descends from the American Medical Association's 1966 Standard Nomenclature of Athletic Injuries, and it characterised sprains on indirect evidence: history, symptoms, physical examination. That is a historical attribution rather than a quotation — the 1966 text could not be obtained, and its definitions circulate now only through retellings.
What can be quoted is what orthopaedic authors have since said about it. A 2018 paper on medial collateral ligament classification describes the AMA scheme as "rather confusing because of difficulty in comparison of treatment results".
So the lineage runs like this: a 1966 clinical nomenclature built without imaging, still spoken aloud in gyms in 2026, sitting alongside two imaging-based systems built in the 2010s specifically because the older one did not carry enough prognostic information. When a physio says "Grade II" and a fighter hears a number, there is a real chance those two people are not even referring to the same classification.
The correlation between grade and time out is weak
Here is the study that most directly answers the question.
Tears and colleagues took 39 hamstring strains from one professional English football club — retrospective, all male professionals — and had two musculoskeletal radiologists re-read the MRIs. They then asked how well the classification predicted return to play.
BAMIC grade correlated with return to play at r = 0.32, 95% CI 0.01 to 0.58, p = 0.05. That is a weak correlation whose confidence interval very nearly includes zero. A multiple regression model including the classification, the maximum length of intramuscular oedema and the percentage cross-sectional area explained 16% of the variance in return to play. Eighty-four percent of what decided the date was something the imaging did not measure. And the grade alone accounted for less than the model did — an r of 0.32 corresponds to about 10% of variance on its own.
The two supporting correlations in the same cohort are, if anything, more striking. Maximum length of intramuscular oedema against return to play: r = 0.3, 95% CI −0.02 to 0.56, p = 0.06. Percentage cross-sectional area against return to play: r = 0.02, 95% CI −0.3 to 0.33, p = 0.91.
Sit with that last one. How much of the muscle was involved had essentially no relationship with how long the athlete was out. In a cohort of 39, in one club, in male professional footballers — the conditions matter and are stated — the single measurement that most closely resembles the intuitive picture of "how bad is it" carried almost no information about the answer.
And in one cohort there was no relationship at all
Hollabaugh and colleagues applied BAMIC to collegiate American football: 24 hamstring and 10 quadriceps tears in 21 of 121 athletes at one institution over the 2023 season, mean age 20 ± 1.2 years, 100% male, MRI within seven days, 89.3% of injuries occurring in preseason and all of them in practice.
Their finding, in their own words: "There was no significant relationship between BAMIC and TRTP, although TRTP was less for grade 0 injuries and greater TRTP for injury site 'c,' albeit with small effect sizes."
The overall median time to return to play was 26 days, with an interquartile range of 17.8 to 33.0 days. The reinjury rate was 19.0% (4 of 21), and 75% of those reinjuries happened before return to play. The authors' summary sentence is the one to carry: "Injured athletes missed about 3 to 4 games, regardless of BAMIC, with 1 in 5 athletes suffering a reinjury."
This is a small, single-institution, level 3 study, and it should not be treated as overturning the studies that did find relationships. It should be treated as what it is: evidence that in a real cohort with real medical support, the grade did not separate the fast returns from the slow ones.
The spread inside one grade
The dispersion is the part that does the argumentative work, and it shows up even in the cohorts that found the strongest grade effects.
McAleer and colleagues followed 38 rectus femoris injuries in 27 elite track and field athletes (mean age 24.7 ± 2.3 years; 10 male, 17 female) from 2010 to 2019, with MRI within seven days of onset. Average time to return to full training for rehabilitation-managed cases: 20.4 ± 14.8 days. The standard deviation is roughly 73% of the mean. One standard deviation either side of that average spans from under a week to over five weeks — inside a single, highly controlled dataset.
Pollock and colleagues' four-year study of 70 hamstring injuries in 46 elite track and field athletes (24 women, 22 men, mean age 24.6 ± 3.7 years) on the British Athletics World Class Programme, December 2015 to November 2019, all MRI-confirmed and all rehabilitated under one prescribed protocol, reported a whole-cohort mean time to return to full training of 18.6 days. Broken out, the intratendon classifications took 34 ± 7 days for 2c and 48 ± 17 days for 3c.
That ±17 days on 3c is a one-standard-deviation band roughly a month wide within a single class, in the most tightly controlled muscle-injury cohort in this literature. The overall reinjury rate in that cohort was 2.9%, with no reinjuries in the intratendon classes — a number that is explicitly a product of the British Athletics rehabilitation approach, and therefore not a number an athlete without that infrastructure has any reason to expect.
The general shape, then: the between-grade differences are real and sometimes large, and the within-grade spread is comparable to or larger than them. A grade moves the centre of a distribution. It does not narrow it enough to produce a date.
Grade is not nothing
The opposite error is available and equally unsupported, so it is worth stating the counter-evidence plainly.
In the rectus femoris cohort, grade 1 injuries had significantly shorter time to return to full training than grade 2 (p = 0.04) and grade 3 (p = 0.01). Intratendinous ('c') injuries and surgically managed cases took significantly longer (p < 0.001). Grade 3 injuries had an increased repeat-injury rate compared with other grades (p = 0.02), and myofascial ('a') injuries had a reduced repeat-injury rate compared with 'b' or 'c' (p = 0.048).
In the British Athletics hamstring cohort, the intratendon classes took roughly double the whole-cohort mean.
And a 2025 scoping review — Medline and SPORTDiscus, 1 January 2010 to 19 April 2022, 13,426 records screened down to 37 included studies, "most of which had low evidence study designs", covering sporting adults with acute non-contact muscle injuries — identified 24 classification systems, of which the six most cited (BAMIC, modified Peetrons, Munich, Cohen, Chan and MLG-R) accounted for 70% of reports. Significant grading-to-return relationships were reported for BAMIC, modified Peetrons, Munich and Cohen. Other classifications reported none, very few, or inconclusive associations.
The review's own summary of the state of the field is the honest one: "There is no agreed-upon use of muscle classification, and no consensus on definitions and terminology. As a result, reported outcomes and their relationship to severity grading are inconsistent across studies. There is a need to improve the generalizability and applicability of existing classifications and to refine their prognostic value."
So: grade shifts the distribution; it does not name a date. Both halves of that sentence are load-bearing.
Two radiologists, the same scan, different grades
If the grade were at least a stable label, a fighter could at minimum treat it as a fixed fact about their body. It is less fixed than that.
A 2025 study in Skeletal Radiology took 111 acute muscle injuries in 110 patients (84% male, mean age 31.8 years), imaged at 1.5T and 3.0T, and had four fellowship-trained musculoskeletal radiologists with 13 to 27 years of experience independently classify them. Inter-reader agreement, expressed as kappa:
- MCIC: 0.566 (95% CI 0.549–0.584)
- BAMIC: 0.506 (95% CI 0.499–0.514)
- CIC: 0.306 (95% CI 0.302–0.311)
The paper's own framing: "The MCIC and BAMIC demonstrate moderate inter-reader reliability, whereas the CIC demonstrates fair inter-reader reliability."
Then there is the between-systems figure from the professional football cohort: BAMIC and Peetrons applied to the same 39 MRIs agreed at kappa 0.21, 95% CI 0 to 0.42. Two accepted grading systems, the same images, agreement that is close to chance.
The failure mode identified in the Skeletal Radiology paper is the sharpest detail in this whole article: "The challenge with the classifications is the reproducibility of localizing the injury anatomically within the muscle, rather than classifying injury severity."
In other words, the part experts disagree about most is the letter — the myofascial / musculo-tendinous / intratendinous localisation. And the letter is the coordinate that carried the largest prognostic weight in both track and field cohorts. The number is the more reproducible half and the less informative half; the letter is the more informative half and the less reproducible half.
One thing this section cannot do is extend the argument to hands-on grading. Every reliability figure above is fellowship-trained radiologists reading MRI. There is no equivalent statistic anywhere for a non-imaging, palpation-based grade assigned by a physio, a coach, a corner or an app. The argument for why a grade recorded without imaging is a different object has to be made structurally — BAMIC and Munich are defined by MRI features, so a grade assigned without a scan is not the thing the system describes — and not with an invented number.
What severity actually means in the literature
The word "severity" is used loosely in gyms and precisely in the surveillance literature, and the precise version is the one that answers the fighter's question.
The IOC's 2020 consensus statement on methods for recording and reporting epidemiological data on injury and illness in sport — produced by a working group, an open online survey and a three-day consensus meeting in October 2019, and verified as current with no superseding general IOC statement located on 7 September 2026 — instructs investigators to "record severity as the number of days that the athlete is unavailable for training and competition, from the date of onset until the athlete is fully available for training and competition".
The counting rule is stated too: "The number of time-loss days should be counted from the day after the onset that the athlete is unable to participate (day 1) through the day before the athlete is fully available for training and competition."
And the reporting rule, which is the statistically interesting part: "severity should be reported as the total number of time-loss days, together with medians and quartiles. Means and standard deviations should be interpreted with care, given that the distribution of time-loss days is likely to be right-skewed."
That last sentence explains a pattern visible across every cohort in this article. The collegiate American football study reports a median and an interquartile range; the track and field studies report means and standard deviations. Because the distribution is right-skewed, those means understate the tail. The 20.4-day rectus femoris average is not the middle of a symmetric spread — it sits to the left of a long right-hand tail of slow returns.
Two facts about severity follow, and they are the ones to take away. First, severity is measured in days, not in tissue. Second, it is measured retrospectively. It is not available on the day of the injury, because the quantity being measured has not finished happening.
The five-label IOC scheme is a misattribution
This one is worth its own section because it circulates widely and is wrong.
You will often read that the IOC classifies injuries as slight, minimal, mild, moderate and severe. The 2020 consensus does not. It recommends continuous time-loss days, and where categorisation is unavoidable it gives four bands: 0 days, 1–7 days, 8–28 days, and more than 28 days.
The five-label scheme belongs to a different and older lineage — the 2006 football (soccer) consensus statement on injury definitions and data collection procedures, which used day bands of minimal 1–3, mild 4–7, moderate 8–28 and severe more than 28. Those bands are reported here with a hedge: the primary publication was paywalled at every endpoint tried, and the bands were confirmed through two independent secondary summaries rather than read in the original. The commonly quoted "slight = 0 days" category could not be confirmed at all and is not printed as fact.
The practical consequence is small but real. If a fighter's medical team is using the current IOC framing and a coach is using the football labels, "moderate" means something in one vocabulary and nothing in the other. And neither vocabulary is a tissue grade — both are ways of bucketing days off, which is the other axis entirely.
What combat sports commissions actually do
Here the article gets to a finding that is stronger than expected, and it is a negative one.
The ABC Unified Rules of Mixed Martial Arts — as approved in April 2001 and amended through the "nonsubstantial changes" of 6 August 2025 — contain the word "suspension" zero times. That was verified by downloading the current PDF and extracting its full text on 7 September 2026. The amendment chain printed on the cover runs 2001, 2010, 3 August 2016, 26 July 2017, 1 August 2018, 1 August 2019, 1 August 2023, 23 July 2024 (implementation November 2024) and 6 August 2025.
Medical suspensions in MMA are therefore not set by the unified ruleset at all. They are set by state and provincial regulation. Anyone who tells you the Unified Rules impose a 30- or 60-day suspension after a knockout is quoting the wrong document — those figures come from the boxing guidelines and from state regulation. If you want the general shape of how rules in this sport are written and amended, the rules coverage on this site is a better starting point than any single summary.
The ABC's regulatory guidelines for professional boxing do carry suspension provisions, and they are explicit: "A boxer losing by way of a Technical Knock Out (TKO) resulting from head blows shall receive a medical suspension and shall not participate in any boxing activity for a minimum period of thirty (30) days. A boxer losing by way of a Knock Out (KO) shall receive a medical suspension and shall not participate in any boxing activity for a minimum period of sixty days. At the discretion of the physician, longer suspension periods may be issued for either the TKO or KO." Separately: "Boxers shall receive a mandatory seven-day rest period after competing in an event. Day 1 of the mandatory rest period shall commence on the first day following the event." And, decisively: "In any/all cases, the decision by the physician to issue or extend a suspension is final."
Nevada's administrative code frames it as a status rather than a period. NAC 467.562: "A licensee who is determined by a physician to be unfit to compete or officiate must be suspended until it is shown that he or she is fit for further competition or officiating." A combatant suspended 30 days for medical protection "shall take a medical examination upon the direction of the Commission or the Commission's representative", and "[t]he examining physician may require any procedures during the medical examination, including an electroencephalogram if indicated."
California's rule for boxers knocked out places the boxer on the commission's ill and unavailable list "for such a period of time as may be recommended by the ringside physician or any approved commission physician who may examine him or her but such period of time shall not be less than 30 days", and states that "[a] boxer shall not be permitted to engage in any contact boxing during this period without the approval of the commission physician." That is a fact about how the regulation is drafted; it is not a route around a suspension, and the approval named in the rule belongs to the commission physician and to nobody else.
Suspensions also travel. Nevada may honour a suspension issued by another jurisdiction where it was ordered for medical safety, and the ABC boxing guidelines state that "[a]ll medical and administrative suspensions placed on contestants by other athletic commissions will be recognized by the supervising Commission."
Now read the whole structure back. Not one of these instruments asks what grade the tissue was. Every one of them is built out of two components: an outcome-triggered minimum period, and a physician's judgement of fitness that can extend it and that holds the release. No commission anywhere in the sources checked keys a suspension to a tissue grade. That absence was searched for and not found, and it is a positive finding, not a gap.
The regulators arrived at the same conclusion this article is making, decades earlier, by a different route.
What replaces the grade in the decision
If the grade cannot produce a date, and severity is only knowable afterwards, what does a clinician actually use?
The 2016 Bern consensus statement on return to sport, produced by 17 expert clinicians at a half-day meeting after the First World Congress in Sports Physical Therapy, reframes the question. "Return to sport is not a decision taken in isolation at the end of the recovery and rehabilitation process. Instead, return to sport should be viewed as a continuum, paralleled with recovery and rehabilitation." And: deciding when to return "is complex and multifactorial—an exercise in risk management".
The Bern group is also candid about the evidence behind its own recommendation: "Research evidence to support return to sport decisions in clinical practice is scarce."
One decision framework the Bern statement points to is StARRT — Strategic Assessment of Risk and Risk Tolerance. Its structure, described here from indexing summaries rather than the primary text, which could not be read in a machine-readable form, runs in three steps: assess tissue health and capacity; assess the tissue stresses imposed by the specific sport activity; and assess risk tolerance. Return is permitted when the risk arising from the first two falls below the threshold set by the third.
For a fighter, step two is where the whole thing turns. "The specific sport activity" is not a generic load. A hamstring at the same grade meets a shot defence, a scramble off the fence, and a switch kick as three completely different tissue-stress questions carrying one label. And step three — risk tolerance — is not a property of the tissue at all. It belongs to the athlete, the clinician and, where a bout and a licence are involved, the commission. Two fighters with identical scans and different fights on different dates can correctly receive different answers.
This is also the reason the load side of the picture matters as much as the imaging side. What the athlete is being asked to absorb on the way back is a measurable quantity, and training load monitoring through a camp is a more tractable input to that judgement than any re-reading of the original scan.
Two hypothetical hamstrings, same grade
A worked scenario, framed explicitly as one. Two hypothetical hamstring injuries, both graded the same, in the same gym. Neither is a real person and neither is a client.
One: the grade is one coordinate, not two. In BAMIC the number is paired with a letter for where — myofascial, musculo-tendinous, intratendinous. In the British Athletics track and field cohort the intratendon classes took 34 ± 7 days (2c) and 48 ± 17 days (3c) against a whole-cohort mean of 18.6 days. Same numeral, different letter, roughly double the time out. A fighter told "Grade II" and nothing else is missing the coordinate that moved the number most.
Two: the spread inside one grade is bigger than expected. Rectus femoris: 20.4 ± 14.8 days. Collegiate American football: median 26 days, IQR 17.8–33.0, and no significant grade-to-time relationship at all. Professional football: r = 0.32 with a confidence interval whose floor touches zero, and a full model explaining 16% of variance.
Three: the label is less stable than it sounds. Kappa 0.506 and 0.566 among four fellowship-trained MSK radiologists reading the same 111 MRIs; kappa 0.21 between two systems reading the same 39. And what they disagree about most is the localisation — the letter from point one.
Four: the axis that answers the actual question is a different one. Days unavailable, counted from the day after onset through the day before full availability, reported as medians and quartiles. Known afterwards. What stands in for it in advance is not a better grade but a decision process: return as a continuum, an exercise in risk management, structured as tissue capacity against sport-specific stress against tolerance for risk.
Five: the sport has already answered this. No commission asks for a grade. Nevada suspends until fitness is shown. California's minimum bans contact and hands the release to the commission physician. The ABC's minimums are floors a physician may extend, and the physician's decision is final. And the Unified Rules of MMA do not mention suspension at all.
What the app records instead, and why
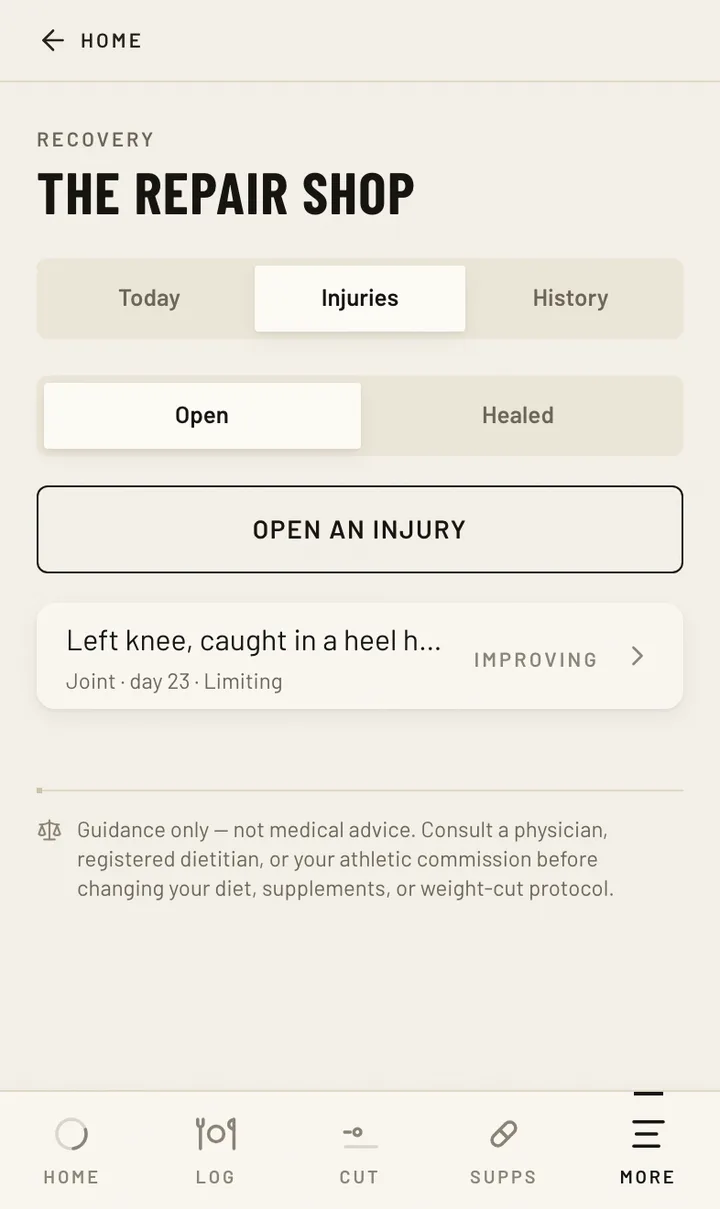
That screen is one design decision, and it is this article's thesis rendered as an interface. The severity field offers three values — niggle, limiting, stopped — which are statements about what the athlete could and could not do. There is no grade field. There is no place to type "II".
The reason is not squeamishness about medical language. It is that the two axes are held by different people. Grading tissue is a diagnosis, made by a clinician, and in these systems made from an image. An athlete's own log cannot produce one, and a field that invited them to guess would produce a number with the authority of a diagnosis and none of the basis for it. What an athlete can record, honestly and daily, is whether the session happened, whether it was modified, and whether the thing is getting better or worse — which is the raw material of the time-loss measurement the surveillance literature actually asks for.
It also keeps the record useful for the person who does hold the other axis. A physician or physio arriving at day 24 of a knee problem is better served by an unbroken record of what training was possible than by an athlete's recollection of a grade they were told once.
The same logic runs through everything else that changes when a fighter gets hurt mid-camp — including what an injury does to a weight cut, where the decision similarly stops being the athlete's alone.
What we could not verify
Several things in this article's territory could not be established, and the shape of the gaps matters as much as the findings.
There is no grade-to-return-to-play cohort in any combat sport. Not in MMA, boxing, Muay Thai, BJJ, wrestling or judo. The entire grade-versus-prognosis evidence base cited here is football, track and field and collegiate American football. The combat-sports literature located instead is injury-rate epidemiology — a 2025 systematic review of 43 reports found post-Unified-Rules MMA competition injury rates ranging from 23.6 to 54.5 injuries per 100 athlete-exposures, a range the review itself attributes partly to reports varying "widely in design, injury definitions, and data collection methods" — and one survey, in which 331 of 360 (92%) self-selected Italian BJJ athletes reported at least one injury, most often to the knee, with 65% returning to training within a month. That is self-reported recall with no imaging and no grading, and it describes what a grappling population did, not what anyone should do.
Adolescents are absent entirely. Every cohort here is adult, with means from 20 to 31.8 years. Nothing transfers to youth wrestling or junior judo, where growth-plate and apophyseal injuries are a different problem that these grading systems were never built to describe.
Amateurs are absent from the grading evidence. Every muscle-injury cohort is elite or collegiate-scholarship, with daily medical staff, MRI within seven days and prescribed rehabilitation. The 2.9% reinjury rate in the British Athletics cohort is explicitly a result of that programme. An athlete without that infrastructure has no basis for expecting it.
No figure here is disaggregated by sex. Two cohorts have meaningful female representation — 24 of 46 athletes in the British Athletics hamstring study, 17 of 27 in the rectus femoris study — but neither reports outcomes separately for women. The professional football cohort, the collegiate American football cohort (100% male) and the radiology cohort (84% male) are male or near-male. The single female-specific observation available is descriptive and tiny: all four complete (4c) proximal free tendon rectus femoris injuries were sustained during sprinting and all were in female athletes, out of 38 injuries. That is n = 4. It is not a rate, and the differences between male and female athletes here are not adjustable with a coefficient.
No reliability statistic exists for non-imaging, hands-on grading. Every kappa in this article is fellowship-trained MSK radiologists reading MRI. There is no published inter-rater figure for a grade assigned by palpation, by a coach, or by any non-clinician. The scope-of-practice argument in this article is therefore made structurally, from the fact that these systems are defined by imaging features, and not from an invented number.
Nothing here is a trial. There is no randomised evidence anywhere in this material that grade-guided rehabilitation beats function-guided rehabilitation. The strongest designs are retrospective cohorts and consensus statements, and the scoping review notes that most of its included studies had low-evidence designs.
The AMA's 1966 Standard Nomenclature of Athletic Injuries could not be obtained. Its grade I/II/III sprain definitions circulate only through secondary retellings, which is why this article attributes the lineage historically and quotes nothing from it.
The 2006 football consensus primary was paywalled at every endpoint tried, returning 402 and 403 responses. Its day bands are reported here as secondary-confirmed only, and the "slight = 0 days" category is not printed at all. And to state the correction plainly one more time: the slight / minimal / mild / moderate / severe scheme is routinely misattributed to the IOC. It is not the IOC's. The current IOC recommendation is continuous days, with 0 / 1–7 / 8–28 / >28 as the fallback bands.
The StARRT primary could not be read. Both PDF mirrors returned raw binary, so its three-step structure is described here from indexing summaries and no sentence of it is quoted.
No published commission schedule keys suspension length to a tissue grade. The ABC, Nevada and California instruments were all searched. The consistent structure is an event-outcome minimum plus a physician's fitness judgement. That absence is reported here as a finding rather than as a hole.
Questions fighters ask
What does Grade II actually mean?
It depends entirely on which system produced it, and it is a statement about tissue, not about time. In the Munich classification, a type 3B — moderate partial tear — is defined as a tear with a diameter greater than a muscle fascicle or bundle, measured on imaging. In the British Athletics classification, a grade 2 is one point on an 0-to-4 MRI scale that also carries a letter for anatomical site. In the older three-grade sprain scheme descended from a 1966 clinical nomenclature, "grade II" meant a moderate injury assessed by history and physical examination, without imaging. None of those definitions contains a number of days, and none defines the grade by a percentage of the muscle.
How long will I be out?
Nobody can tell you from a grade, and the honest version of the answer is that the person who examined the limb is the only one who should be estimating it for you. The published figures give a sense of scale rather than a prediction: 20.4 ± 14.8 days for rehabilitation-managed rectus femoris injuries in 27 elite track and field athletes; a median of 26 days with an interquartile range of 17.8 to 33.0 in collegiate American footballers; a whole-cohort mean of 18.6 days for hamstrings in a British Athletics programme. All of those come from athletes with daily medical supervision and prescribed rehabilitation, in sports that are not combat sports.
Is it true that Grade I is two weeks, Grade II is four to six, and Grade III is three months?
No, and that timetable does not trace to a primary source. It is contradicted by the actual dispersion in the literature: a standard deviation of 14.8 days on a 20.4-day mean in one cohort, a one-standard-deviation band 34 days wide on a single intratendon class in another, and an outright null result — no significant relationship between grade and time to return — in collegiate American football. The folk timetable survives because it is memorable, not because anyone measured it.
Does the grade tell my coach anything at all?
Yes, but less than it sounds and in a different form than a date. Grade 1 rectus femoris injuries returned significantly faster than grade 2 (p = 0.04) and grade 3 (p = 0.01) in one elite track and field cohort; grade 3 injuries reinjured more often (p = 0.02); intratendinous involvement took significantly longer (p < 0.001). A scoping review found significant grading-to-return relationships for four of the six most-cited systems. The correct reading is that grade shifts the distribution of likely outcomes without narrowing it enough to give a date.
How reliable is the grade itself?
Moderately, among experts with the images in front of them. Four fellowship-trained musculoskeletal radiologists with 13 to 27 years of experience, reading 111 acute muscle injury MRIs, agreed at kappa 0.506 for BAMIC and 0.566 for the Munich classification — described by the authors as moderate reliability. In a separate cohort, two accepted grading systems applied to the same 39 MRIs agreed at kappa 0.21, which is close to chance. The specific thing readers disagree about most is localising the injury anatomically within the muscle, not classifying its severity.
Does a Grade II mean the muscle is 50% torn?
No source in this material defines any grade by a percentage of muscle cross-section. The Munich 3A/3B boundary is a fascicle-width threshold on imaging; the British Athletics system is a grade plus an anatomical site letter. And the percentage cross-sectional area involved had essentially no correlation with return to play in the one study that measured it against time out — r = 0.02, 95% CI −0.3 to 0.33, p = 0.91, in 39 hamstring strains in male professional footballers.
What does "severity" mean in a research paper?
Days unavailable. The IOC's 2020 consensus on recording injury and illness data instructs investigators to record severity as the number of days the athlete is unavailable for training and competition, from the date of onset until they are fully available again, counted from the day after onset through the day before full availability. It further recommends reporting the total with medians and quartiles, because the distribution of time-loss days is likely to be right-skewed and means will understate the tail.
Does the IOC use slight, minimal, mild, moderate and severe?
No. That is a common misattribution. The 2020 IOC consensus recommends recording severity as continuous days unavailable, and where categorisation is unavoidable it gives four bands: 0 days, 1 to 7 days, 8 to 28 days, and more than 28 days. The five-label scheme belongs to the older football-consensus lineage from 2006, which used minimal 1–3 days, mild 4–7, moderate 8–28 and severe over 28 — bands reported here from secondary summaries because the primary was paywalled.
Do the Unified Rules of MMA set a suspension after a knockout?
No. The ABC Unified Rules of Mixed Martial Arts, as approved in April 2001 and amended through 6 August 2025, contain the word "suspension" zero times — verified by full-text extraction of the current document on 7 September 2026. Medical suspensions in MMA are set by state and provincial regulation instead. The 30-day and 60-day figures that get quoted come from the ABC's regulatory guidelines for professional boxing and from state rules, not from the MMA ruleset.
Will a commission ask for my injury grade?
Nothing found in the ABC guidelines, Nevada's administrative code or California's regulations keys a suspension or a clearance to a tissue grade. The consistent structure is an event-outcome minimum period plus a physician's judgement of fitness. Nevada suspends an unfit licensee "until it is shown that he or she is fit"; California's knockout rule sets a minimum of not less than 30 days with the commission physician holding the release; the ABC states that a physician's decision to issue or extend a suspension is final.
Is a medical suspension a healing timetable?
No, and treating it as one is a category error. These are risk-management floors that follow an event outcome — usually head trauma — rather than assessments of any particular tissue. They set a minimum that a physician may extend, and in Nevada's framing the suspension runs until fitness is demonstrated rather than until a clock expires. A suspension says nothing about a hamstring, and a hamstring's grade says nothing about a suspension.
If the grade does not decide, what does?
A decision process rather than a measurement. The 2016 Bern consensus describes return to sport as a continuum paralleling rehabilitation and as "an exercise in risk management", while conceding that research evidence to support these decisions in clinical practice is scarce. The StARRT framework it points to structures the judgement in three steps: tissue health and capacity, the tissue stresses imposed by the specific sport activity, and risk tolerance. For a fighter the middle step is decisive, because a shot defence, a scramble and a switch kick load the same tissue very differently.
Why does the Fighter Cut injuries screen not have a grade field?
Because grading tissue is a diagnosis, and these grading systems are defined by MRI features — a grade recorded without imaging is not the object the system describes. The app records severity as niggle, limiting or stopped: statements about what the athlete could and could not do in a session. That is also the raw material of the time-loss measurement the surveillance literature actually asks for, and it stays useful to the clinician who does hold the diagnostic axis.
Does any of this evidence come from my sport?
No. There is no muscle-injury grading-to-return-to-play cohort in MMA, boxing, Muay Thai, BJJ, wrestling or judo. Every grade-versus-time figure in this article comes from professional football, elite track and field, or collegiate American football, in adult and mostly male athletes with full-time medical support. The combat-sports literature that does exist here is injury-rate epidemiology and one self-reported survey of BJJ athletes, neither of which grades tissue.
Does any of this apply to a teenage wrestler or judoka?
No. Every cohort cited is adult, with mean ages from 20 to 31.8 years, and adolescents are absent from this material entirely. Growth-plate and apophyseal injuries are a different problem that the muscle-grading systems described here were never built to classify, and adult figures do not scale downward with a coefficient. A young athlete's injury is a question for a clinician who treats young athletes.
Sources
Sourced to
- British athletics muscle injury classification: a new grading system — Pollock N, James SLJ, Lee JC, Chakraverty R, British Journal of Sports Medicine 2014;48(18):1347–51. DOI 10.1136/bjsports-2013-093302, PMID 25031367
- Terminology and classification of muscle injuries in sport: the Munich consensus statement — Mueller-Wohlfahrt H-W, Haensel L, Mithoefer K et al., British Journal of Sports Medicine 2013;47(6):342–50. PMID 23080315, PMC3607100
- The British Athletics Muscle Injury Classification grading system as a predictor of return to play following hamstrings injury in professional football players — Tears C, Rae G, Hide G, Sinha R, Franklin J, Brand P, Hasan F, Chesterton P, Physical Therapy in Sport 2022. DOI 10.1016/j.ptsp.2022.08.002, PMID 36148699
- A 4-year study of hamstring injury outcomes in elite track and field using the British Athletics rehabilitation approach — Pollock N, Kelly S, Lee J, Stone B, Giakoumis M, Polglass G, Brown J, MacDonald B, British Journal of Sports Medicine 2022. DOI 10.1136/bjsports-2020-103791, PMID 33853835
- Time to return to full training and recurrence of rectus femoris injuries in elite track and field athletes 2010–2019; a 9-year study using the British Athletics Muscle Injury Classification — McAleer S, Macdonald B, Lee J, Zhu W, Giakoumis M, Maric T, Kelly S, Brown J, Pollock N, Scandinavian Journal of Medicine & Science in Sports 2022. DOI 10.1111/sms.14160, PMID 35332596
- Application of the British Athletics Muscle Injury Classification in Collegiate Football Athletes: A Retrospective, Observational Study — Hollabaugh W, Hill T, Davidson C, Pennings J, Strasser N, Porras L, Cox C, Fitch R, Sports Health 2025. DOI 10.1177/19417381251326531, PMID 40145663
- Classification systems for assessing acute muscle injuries: a retrospective comparison of inter-reader agreements — Skeletal Radiology 2025;55(1):191–203, published online 13 August 2025. PMC12627197
- Classification of myo-connective tissue injuries for severity grading and return to play prediction: A scoping review — Fontanier V, Bruchard A, Tremblay M et al., Journal of Science and Medicine in Sport 2025. DOI 10.1016/j.jsams.2024.07.016, PMID 39232948
- International Olympic Committee consensus statement: methods for recording and reporting of epidemiological data on injury and illness in sport 2020 (including the STROBE Extension for Sport Injury and Illness Surveillance) — Bahr R, Clarsen B, Derman W et al., British Journal of Sports Medicine 2020;54(7):372–89 / Orthopaedic Journal of Sports Medicine 2020. DOI 10.1177/2325967120902908, PMID 32071062, PMC7029549
- Consensus statement on injury definitions and data collection procedures in studies of football (soccer) injuries — Fuller CW, Ekstrand J, Junge A et al., British Journal of Sports Medicine 2006;40(3):193–201. PMID 16505073. Primary paywalled at the time of writing; day bands reported here from secondary summaries only
- 2016 Consensus statement on return to sport from the First World Congress in Sports Physical Therapy, Bern — Ardern CL, Glasgow P, Schneiders A et al., British Journal of Sports Medicine 2016. DOI 10.1136/bjsports-2016-096278, PMID 27226389
- Strategic Assessment of Risk and Risk Tolerance (StARRT) framework for return-to-play decision-making — Shrier I, British Journal of Sports Medicine 2015;49(20):1311–5. PMID 26036678. Primary not machine-readable; three-step structure described from indexing summaries, nothing quoted
- Medial Collateral Ligament Injury; A New Classification Based on MRI and Clinical Findings — Makhmalbaf H, Shahpari O, Archives of Bone and Joint Surgery 2018;6(1):3–7. PMC5799597
- ABC Unified Rules of Mixed Martial Arts, as approved April 2001 and amended through 6 August 2025 — Association of Boxing Commissions and Combative Sports; PDF downloaded and text-extracted 7 September 2026, containing zero occurrences of the word "suspension"
- ABC Regulatory Guidelines and Rules for All Professional Boxing Competitions in the United States — Association of Boxing Commissions, hosted copy via the BC Athletic Commission; medical-suspension text extracted 7 September 2026
- Nevada Administrative Code Chapter 467 — Unarmed Combat, including NAC 467.562 (Suspension of licensee for medical reason) and NAC 467.888 — Nevada Legislature; in force, retrieved 7 September 2026
- California Code of Regulations Title 4, § 352 — Boxers Knocked Out — California Athletic Commission, amended 30 October 1995; text via Cornell Legal Information Institute
- Injuries in Mixed Martial Arts After Adoption of the Unified Rules of MMA: A Systematic Review — Orthopaedic Journal of Sports Medicine 2025. DOI 10.1177/23259671251342578, PMID 40620723
- Is Brazilian Jiu-Jitsu a Traumatic Sport? Survey on Italian Athletes' Rehabilitation and Return to Sport — Journal of Functional Morphology and Kinesiology 2025. DOI 10.3390/jfmk10030286, PMID 40843817
Read next
Plan the descent, don't guess it
Fighter Cut builds a week-by-week plan from today to your weigh-in, classifies the rate you are actually losing at, and logs what you eat against it. It does not make a cut safe — nothing does. It makes the numbers visible early enough to change them.
Open Fighter Cut